
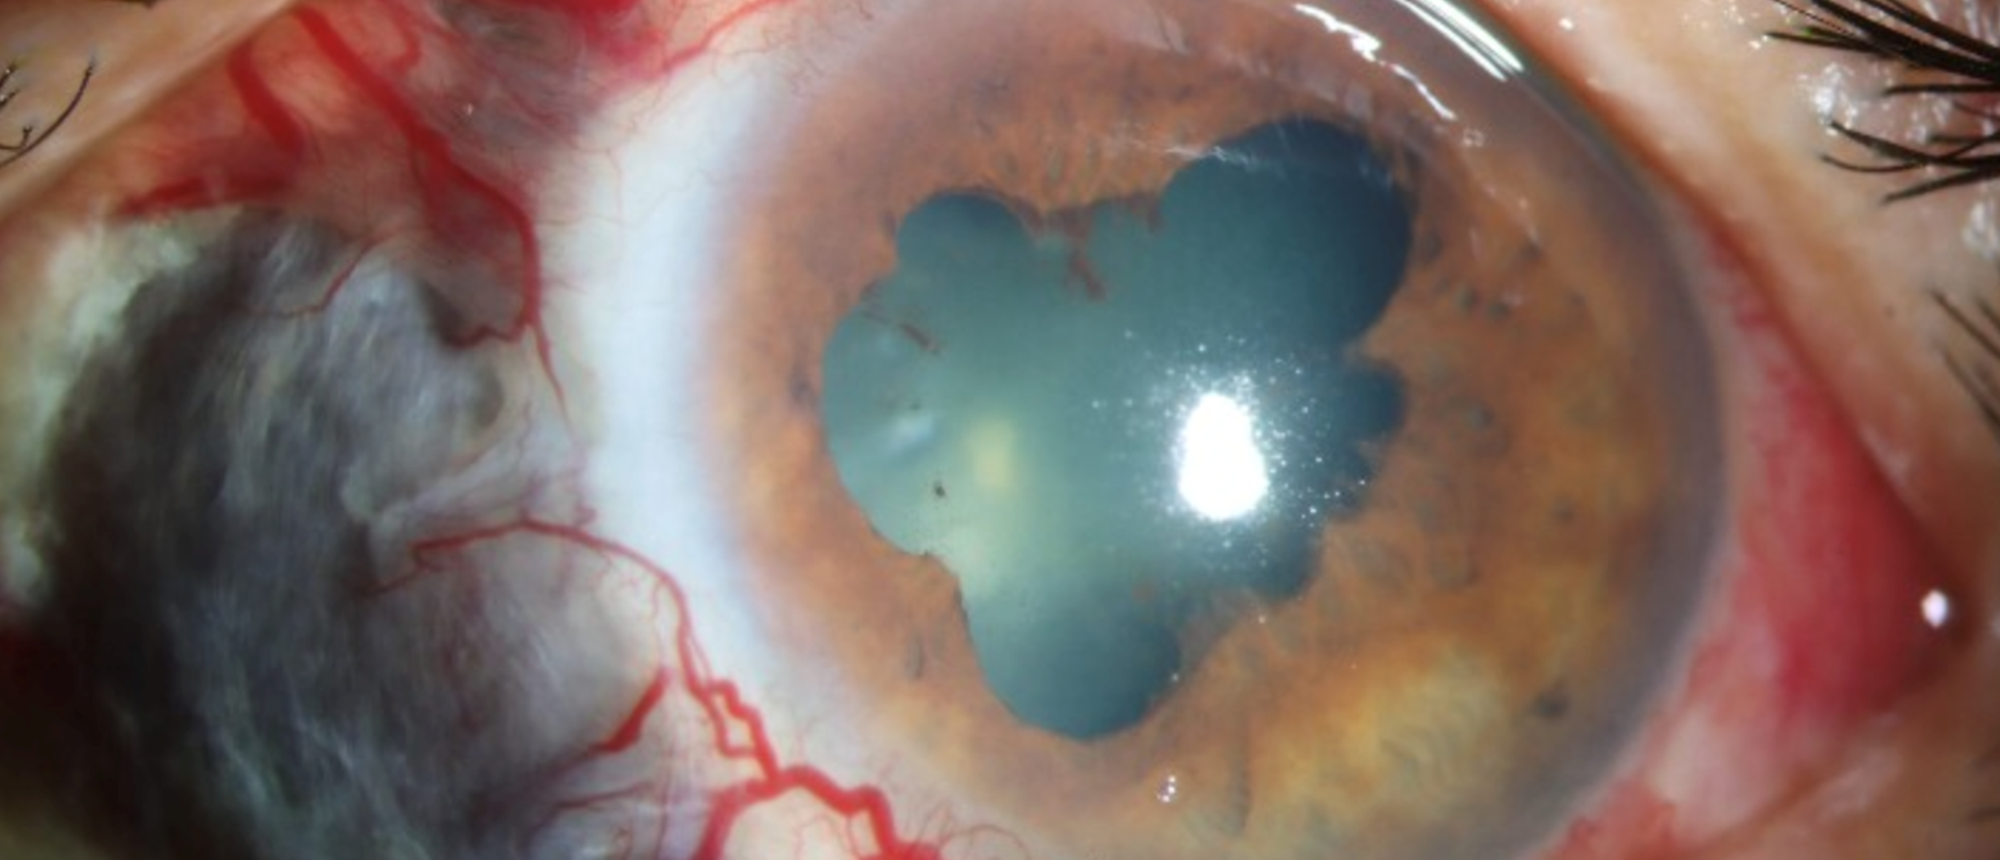
Infectious Necrotising Scleritis
A patient with a remote history of bilateral pterygium excision presented to the Bascom Palmer Emergency Room with three weeks of worsening left eye pain and decreased vision. Initial visual acuity was 20/40 in the affected eye with an intraocular pressure of 12 mmHg. Anterior segment examination demonstrated marked conjunctival injection, two areas of nasal scleral melt with uveal show, mild anterior chamber inflammation, mutton-fat keratic precipitates, and 360-degree posterior synechiae. Posterior segment evaluation revealed a supratemporal choroidal detachment with associated subretinal fluid and an inferior serous retinal detachment. Prior systemic evaluation, including QuantiFERON, RPR, ANA, ANCA, lysozyme, and rheumatoid factor, was unrevealing. Given concern for an infectious process, scleral cultures were obtained and intensive fortified topical antibiotics were initiated while the differential diagnosis remained broad. This case highlights the diagnostic challenge of distinguishing infectious from immune-mediated and postoperative causes of progressive scleral necrosis. The subsequent discussion focuses on indications and timing for surgical intervention, evidence comparing medical therapy alone with combined medical-surgical management, and adjunctive treatment strategies for refractory disease, including subpalpebral antibiotic lavage and Rose Bengal photodynamic antimicrobial therapy.
Presentation Date: 10/01/2026
Issue Date: 10/02/2026
Please log in or click on ENROLL ME to access this course.
